

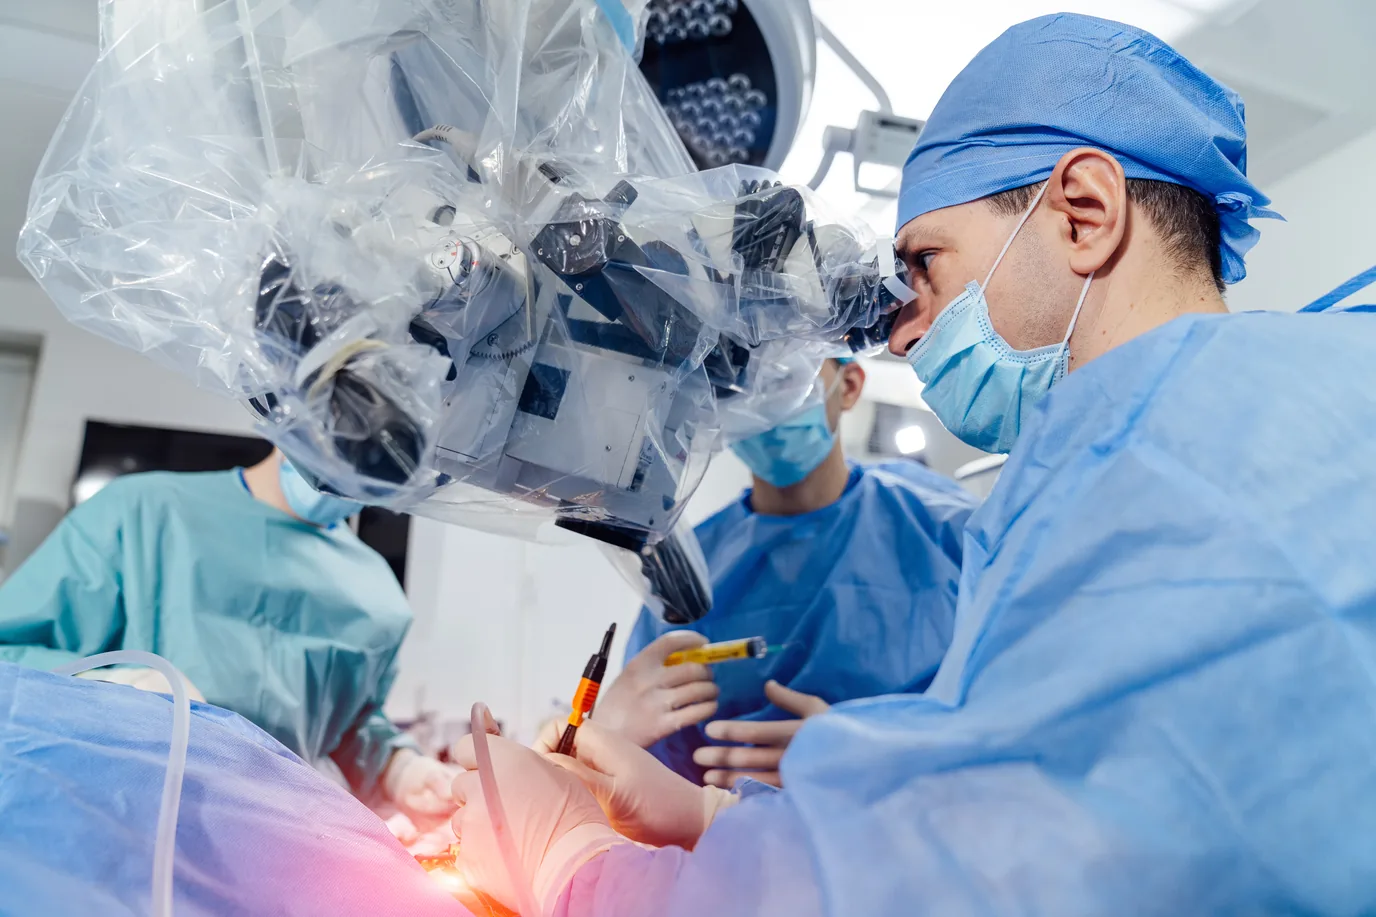
Hearing the words "you may need an operation" for your back or neck can be frightening. Many people who come to me to discuss spine surgery in Hyderabad arrive with a thick file of reports, advice from several relatives and a lot of fear. I am Dr. Praveen Goparaju, a Consultant Minimally Invasive and Deformity Spine Surgeon at CARE Hospitals, HITEC City and DIA Clinics, Kokapet. In this article I explain, in plain language, what spine surgery is, the main types, who really needs it, and how to prepare, so that you can make a calm and informed decision with your family.
What is spine surgery?
The spine is a column of small bones called vertebrae, stacked from the neck down to the lower back. Between them sit soft, cushion-like discs. Through the middle runs the spinal canal, which protects the spinal cord and the nerves that branch out to the arms and legs.
Spine surgery is any operation on these structures. Almost every spine operation does one or more of three jobs:
- Free a trapped nerve or the spinal cord (decompression), for example by removing a piece of slipped disc or thickened bone and ligament that is pressing on it.
- Make an unstable spine steady (stabilisation or fusion), usually with screws, rods and bone graft, so that two or more vertebrae heal into one solid piece.
- Correct the shape of the spine (deformity correction), for a sideways curve or a forward stoop that causes pain and imbalance.
Fixing a broken vertebra, treating a spinal infection or removing a tumour uses the same basic ideas of decompression and stabilisation.
Most back pain does not need surgery
This is the most important point in this article. Most episodes of back pain and neck pain settle within a few weeks with relative rest from activities that worsen the pain, medicines prescribed by a doctor, physiotherapy and better posture. Even many slipped discs shrink on their own over weeks to months.
An MRI report can also look alarming. Words such as "disc bulge", "degeneration" or "desiccation" appear in the scans of many people who have no pain at all, especially after the age of forty. A scan finding on its own is not a reason for an operation. What matters is whether the scan matches your symptoms and what your doctor finds when examining you.
For many people, a planned course of non-surgical treatment, sometimes with an injection such as a nerve root block, is the right first step. Our pain management services page explains these options.
Who actually needs spine surgery?
Surgery is usually considered for a smaller group of people:
- Leg or arm pain from a trapped nerve, such as sciatica from a slipped disc, that has not improved after six to twelve weeks of good non-surgical care, or that is so severe it stops normal life.
- Weakness or numbness that is getting worse, such as a foot that drags or a hand that keeps dropping things.
- Spinal stenosis, where narrowing of the canal makes walking even short distances painful, and other treatment has not helped.
- Spondylolisthesis or instability, where one vertebra slips forward on another and causes ongoing pain or nerve symptoms.
- Pressure on the spinal cord in the neck (cervical myelopathy), which can cause clumsy hands, difficulty with buttons and unsteady walking.
- Fractures of the spine after a fall, a road accident or weak bones, especially when the fracture is unstable.
- Deformity such as scoliosis or kyphosis that is getting worse or causing pain and imbalance.
- Infection or tumour affecting the spine.
- Emergencies such as cauda equina syndrome, where sudden loss of bladder or bowel control and numbness in the private-part area need surgery within hours.
Even within these groups, the decision is personal: your age, health, work and goals all matter.
Types of spine surgery in Hyderabad
The right operation depends on your exact problem, not on what a friend or relative had done.
| Operation | What it does | Usually considered for |
|---|---|---|
| Microdiscectomy | Removes the part of a slipped disc pressing on a nerve, using a microscope through a small cut | Sciatica or arm pain from a disc |
| Endoscopic (keyhole) discectomy | Removes the disc fragment using a thin camera through a very small cut | Selected disc problems |
| Decompression (laminectomy or laminotomy) | Removes thickened bone and ligament to widen a narrow spinal canal | Spinal stenosis |
| Spinal fusion (for example TLIF or ACDF) | Joins two or more vertebrae with screws, a cage and bone graft | Instability, slipped vertebra, some disc problems |
| Disc replacement | Replaces a worn disc with an artificial disc that keeps movement | Selected neck and lower-back disc problems |
| Deformity correction | Straightens and balances the spine with rods and screws, sometimes with bone cuts (osteotomy) | Scoliosis, kyphosis, adult spinal deformity |
| Fracture fixation | Holds a broken spine steady with screws and rods while it heals | Unstable spinal fractures |
| Vertebroplasty or kyphoplasty | Injects bone cement into a collapsed vertebra | Painful osteoporotic fractures |
| Revision surgery | Corrects problems that remain or return after an earlier operation | Pain or failure after previous spine surgery |
You can read more about these operations on our pages for disc surgeries and spinal fusion surgeries.
Open and minimally invasive spine surgery
Many spine operations can now be done with minimally invasive methods: smaller cuts, narrow tubes or an endoscope, and less disturbance of the back muscles. For suitable patients, this can mean less pain after surgery, a shorter hospital stay and an earlier return to walking.
Minimally invasive surgery is not right for every problem, though. Large deformities, some complex fractures and some revision operations still need an open approach to do the job safely and completely. The aim is always the right operation done well, not simply the smallest cut. Our article on keyhole vs open spine surgery explains the difference in more detail.
Modern tools such as intraoperative nerve monitoring (neuromonitoring) and navigation are used where suitable. Neuromonitoring keeps a check on the nerves and spinal cord during the operation, and navigation helps guide the placement of screws.
Questions to ask your spine surgeon
A good consultation should leave you clear about your choices. Do not hesitate to ask:
- What exactly is causing my pain, and does my scan match my symptoms?
- What happens if I do not have surgery now? Is it safe to wait?
- Which non-surgical options are still left to try?
- Which operation do you suggest, and why this one rather than another?
- Will it be minimally invasive or open, and how many levels of the spine are involved?
- Will screws or other implants be used?
- What are the main risks for someone of my age and health?
- How long will I stay in hospital, and when can I walk, sit, travel and go back to work?
- What realistic improvement can I expect in pain, walking and daily activity?
- Who will follow me up after surgery, and what physiotherapy will I need?
Write the answers down, or bring a family member along.
Getting a second opinion
Asking for a second opinion is normal and sensible, especially for a planned operation such as a fusion or a deformity correction. A good surgeon will not be offended. Bring all your scans (the actual images on a CD or a link, not only the written reports), earlier prescriptions and a list of the treatments you have already tried.
A second opinion is most useful when you are unsure the diagnosis is right, when you have been advised a large operation mainly for back pain, or when two doctors have told you different things. In an emergency, such as sudden weakness or bladder problems, do not delay treatment to collect opinions.
Preparing for spine surgery
Once you and your surgeon decide on surgery, a little preparation helps your recovery:
- Medical check-up. Blood tests, an ECG and sometimes a chest X-ray or heart check, along with an assessment by the anaesthesia team.
- Control diabetes and blood pressure. Good sugar control lowers the risk of wound infection and helps healing.
- Stop smoking and chewing tobacco. Tobacco slows bone and wound healing, especially after a fusion. Stopping even a few weeks before surgery helps.
- Tell your team about all your medicines, especially blood thinners and any herbal or Ayurvedic preparations. Do not stop any medicine on your own; your doctors will tell you what to pause and when.
- Prepare your home. Keep a firm chair with armrests, a raised toilet seat or Western toilet if possible, and keep things you use every day at waist height.
- Plan support. Arrange for a family member to help for the first few days, and plan leave from work.
When to see a spine surgeon
Book a consultation if:
- back or neck pain lasts longer than six weeks despite treatment,
- pain spreads into a leg or arm, with tingling or numbness,
- you cannot walk as far as before because of leg pain or heaviness,
- you have been advised surgery and want to understand your options,
- you have back pain along with fever, unexplained weight loss or a past history of cancer.
Go to an emergency department straight away if you have new weakness in the legs or arms, numbness in the private-part area, or loss of bladder or bowel control.
I see patients from across Hyderabad, Telangana and Andhra Pradesh at CARE Hospitals, HITEC City and DIA Clinics, Kokapet. You can book a consultation at either location.
Frequently asked questions
Does every slipped disc need spine surgery? No, most slipped discs improve with time, medicines, physiotherapy and sometimes an injection; surgery is kept for pain that does not settle or for nerve weakness.
How do I decide on spine surgery in Hyderabad? Meet a spine surgeon, make sure your scan matches your symptoms, understand the options and risks, and take a second opinion if you are unsure.
Is minimally invasive spine surgery suitable for everyone? No, it suits many disc and stenosis problems, but large deformities and some fractures or revision cases need open surgery.
Should I get a second opinion before spine surgery? It is a sensible step for planned operations such as fusion; bring your actual scan images and earlier treatment records.
Who should I see for advice on back or neck surgery? A consultant spine surgeon such as Dr. Praveen Goparaju can examine you, review your scans and explain whether you need surgery at all.



